Sodium channel blockers are class I antiarrhythmic agents, local anesthetics, and anticonvulsants that reversibly bind to fast voltage-gated Na+ channels to suppress rapid membrane depolarization.
By decreasing Phase 0 upstroke velocity (dV/dt), these drugs slow cardiac conduction velocity, reduce neuronal excitability, and elevate seizure thresholds.
They are categorized into Class IA, IB, and IC antiarrhythmics, as well as local anesthetics and anticonvulsants.
| Class/ Group | Mechanism | Drug Examples | Clinical Indications |
|---|---|---|---|
| Class IA | Moderate block. Intermediate kinetics. Prolongs APD | Quinidine, Procainamide, Disopyramide | Atrial & Ventricular arrhythmias |
| Class IB | Weak block Fast kinetics Shortens APD | Lidocaine, Mexiletine, Phenytoin | Ventricular arrhythmias (ischemic tissue) |
| Class IC | Strong block Slow kinetics Minimal APD effect | Flecainide, Propafenone | Supraventricular arrhythmias (e.g., AF) |
| Local Anesthetics | Blocks open/inactivated channels Stops nerve conduction | Lidocaine, Bupivacaine, Tetracaine | Infiltration, nerve blocks, epidurals |
| Anticonvulsants | Prolongs the inactivated state, inhibits repetitive firing | Carbamazepine, Phenytoin, Lamotrigine | Seizures, neuropathic pain |
Physiology of Voltage-Gated Sodium Channels: State-dependent blocking (Resting vs. Open vs. Inactivated states).
Voltage-gated sodium channels are responsible for the rapid depolarization of the action potential in neurons, cardiac, and other excitable cells.
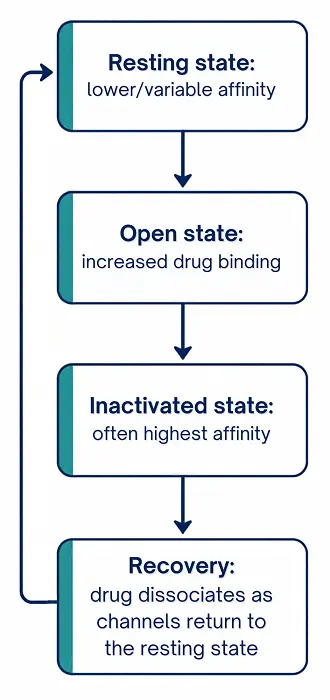
Resting state:
- At the resting membrane potential, the Na+ channel is closed but available for activation.
- The activation gate is closed.
- The channel can open when the membrane is sufficiently depolarized.
- Resting-state blockers preferentially bind to this state.
Example: some local anesthetics and Na+ channel blockers show relatively greater binding when channels are resting.
Open (activated) state:
- Depolarization causes the channel to open rapidly.
- Na+ enters the cell, which causes rapid depolarization.
- The open state lasts only a very short time.
- Drugs that preferentially bind the open channel are called state-dependent or use-dependent blockers.
Inactivated state:
- Shortly after opening, the channel becomes inactivated.
- Na+ cannot pass through the channel even though the membrane is still depolarized.
- The channel must return toward the resting membrane potential before it can become available again.
- Many Na+ channel blockers have a high affinity for the inactivated state.
State-dependent blockade:
A voltage-gated sodium channel exists in three main states:
- Resting (closed and ready),
- Open (active and conducting Na+), and
- Inactivated (temporarily blocked from opening).
Through State-dependent blockade, a drug does not bind to all states equally; it prefers specific channel shapes.
- Most sodium channel blockers show the highest affinity for channels that are Open or Inactivated rather than channels in the Resting state.
- Hence, these drugs target open and inactivated channels; thereby selectively blocking rapidly firing or abnormal cells (like ectopic heartbeats or seizure foci) while leaving normal, resting cells unaffected.
Use dependent blockade:
- The more frequently the channel is activated, the greater the block becomes.
- Repeated depolarization leads to more channels entering open/inactivated states.
- More drug binding occurs.
- With repeated stimulation, progressively fewer Na+ channels are available.
- Therefore, blockade is stronger at high firing rates.
- Example: Class I antiarrhythmic drugs show use-dependent Na+ channel blockade.
Resting state VS Open state VS Inactivated state
| Feature | Resting state | Open state | Inactivate state |
|---|---|---|---|
| Channel state | Closed | Open | Closed/inactivated |
| Na+ movement | No Na+ entry | Na+ enters | No Na+ entry |
| When? | Resting membrane potential | During depolarization | Immediately after opening |
| Availability | Available to open | Active | Unavailable to reopen |
| Drug binding | Lower affinity for many blockers | Higher affinity | Often highest affinity |
| Block significance | Less block | More block | Major state for many blockers |
| Key idea | ready | conducting | Temporarily unavailable |
Sodium Channel Blocking Drugs
Class I Antiarrhythmics (Vaughan Williams Classification):
- Class 1A: Intermediate kinetics (e.g., Quinidine, Procainamide).
- Class 1B: Fast kinetics (e.g., Lidocaine, Mexiletine).
- Class 1C: Slow kinetics (e.g., Flecainide, Propafenone).
Local Anesthetics: Hydrophobic/Intracellular pathway, ester vs. amide drug comparisons.
Anticonvulsants / Neuropathic Agents: Phenytoin, Carbamazepine, Lamotrigine.
Summary Comparison Table: Mapping binding kinetics, action potential duration (APD) effects, and clinical indications.
| Class | Pharmacodynamics & Kinetics | APD effect | Example drugs | Clinical indications. |
|---|---|---|---|---|
| Class IA | Moderate block ⋅ Intermediate dissociation | Prolonged (↑) | Quinidine, Procainamide, Disopyramide | Atrial & Ventricular arrhythmias |
| Class IB | Mild / Weak block ⋅ Fast dissociation | Shortened (↓) | Lidocaine, Mexiletine, Phenytoin | Ventricular arrhythmias (ischemic tissue) |
| Class IC | Strong block, slow dissociation | Minimal Effect (↔) | Flecainide, Propafenone | Supraventricular arrhythmias (e.g., AF) |
| Local Anesthetics | State-dependent (Open/Inactivated) | Blocks nerve conduction | Lidocaine, Bupivacaine, Tetracaine | Infiltration, nerve blocks, epidurals |
| Anticonvulsants | Prolongs inactivated state (Use-dependent) | Reduces repetitive firing | Carbamazepine, Phenytoin, Lamotrigine | Focal/generalized seizures, neuropathic pain |
Classification of sodium channel blocking drugs:
Class 1A:
- Moderate Na+ channel block.
- Main drugs:
- Quinidine
- Procainamide
- Disopyramide
- Decreases conduction and increases action-potential duration.
Class IB:
- Mild/rapid Na+ channel block.
- Main drugs:
- Lidocaine
- Mexiletine
- Decrease the action-potential duration.
Class 1C:
- Strong Na+ channel block.
- Main drugs:
- Flecainide
- Propafenone
- Decreases the conduction velocity.
Mechanism of action
Na+ channel blockers bind to fast voltage-gated Na+ channels and reduce the rapid influx of Na+ during phase 0 of the cardiac action potential.
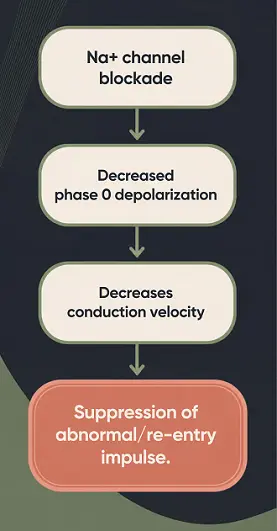
Their effects differ according to the class:
- Class 1B: Mild Na+ blockade that shortens the action potential duration, particularly in ventricular tissue.
- Class 1C: Strong Na+ blockade that markedly slows conduction, with little effect on action potential duration.
- Class 1A: Moderate Na+ blockade and blocks some K+ channels, which leads to the prolonged action potential duration and QT interval.
Local anesthetics
Local anesthetics reversibly block voltage-gated Na+ channels, preventing action-potential generation and propagation.
Classification:
1. Ester-linked local anesthetics:
- Procaine
- Chloroprocaine
- Tetracaine
- Benzocaine
2. Amide-linked local anesthetics:
- Lidocaine
- Mepivacaine
- Prilocaine
- Bupivacaine
- Ropivacaine
- Etidocaine
Mechanism through the Hydrophobic/intracellular pathway:
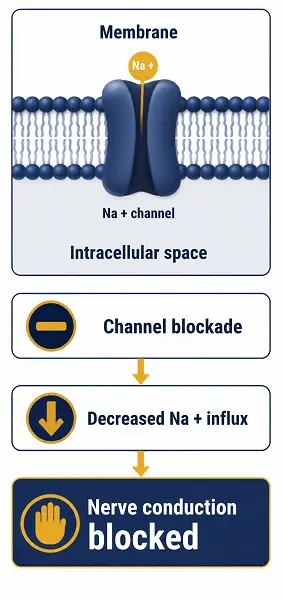
- Most local anesthetics are weak bases and exist in two forms: Ionized and Unionized forms
- Unionized (B) form: the liquid soluble hydrophobic crosses the nerve cell membrane.
- Inside the neuron, some drugs become ionized (B-H+)
- The ionized form accesses the intracellular side of the voltage-gated Na+ channel.
- It binds to the channel, particularly the open/inactivated state.
- Na+ influx decreases, which leads to depolarization and action-potential propagation being blocked.
Uses of local anesthetics:
- Local and regional anesthesia
- Dental procedures
- Minor surgical procedures
- Nerve blocks
- Epidural and spinal anesthesia
- To relieve localized neuropathic pain
- Treatment of some cardiac arrhythmias
Anticonvulsants / neuropathic agents:
Some antiepileptic (anticonvulsant) drugs are also used to treat neuropathic pain because they reduce excessive neuronal excitability.
Classification:
- Sodium (Na+) channel blockers:
- Phenytoin
- Carbamazepine
- Lamotrigine
- Oxcarbazepine
- Lacosamide
Uses of anticonvulsants:
- Epilepsy and seizure disorder
- Neuropathic pain
- Trigeminal neuralgia – carbamazepine
- Diabetic peripheral neuropathy
- Certain other neuralgias and nerve-related pain
- Prevention of seizures in certain neurological conditions.
- Some drugs are also used in bipolar disorder and migraine prevention, depending on the specific drug.
References:
- Pharmacodynamics & Drug Tolerance — voltage-gated ion channels, state-dependent blockade, and cellular pharmacodynamics.
- Voltage-Gated Ion Channels & Receptor Kinetics
- Class I Antiarrhythmics & Local Anesthetic Kinetics — Vaughan-Williams Class IA, IB, and IC dissociation kinetics, action potential duration (APD) effects, and nerve block mechanisms.
- Goodman & Gilman’s — Sodium Channel Blockers & Antiarrhythmic Agents.
- Local Anesthetics Mechanism & Pharmacology
